MTA - an Endodontic Boon in Healing of Periradicular Lesions
Department of Conservative Dentistry and Endodontics, Seema Dental College And Hospital, Rishikesh
INTRODUCTION
An apicoectomy was well defined in 1884 by J. Farrar as “a bold act, which removes the entire cause [of disease] and which will lead to a permanent cure may not be the best in the end, but the most humane.” According to Black,the root-resection technique (amputation of the root apex) originated as a treatment for “pyorrhea alveolaris” complicated by a dental abscess in the late years of the 19th century as a valid alternative to a dental extraction.1
Teeth that are compromised secondary to endodontic failure may be salvaged with endodontic re-treatment. Extirpation of the compromised pulpal tissue and treatment of the localized infection routinely resolve disease and prevent tooth extraction. If periapical pathology persists, however, an adjunctive surgical procedure known as apicoectomy is necessary to eradicate disease and improve the therapeutic outcome. Apicoectomy procedures involve a soft tissue incision and removal of localized disease and frequently require apical sealing of the endodontically treated tooth.3
Re-treatment of a previously endodontically treated tooth may be necessary when signs of failure appear, usually detected radiographically. Most commonly, the first signs are detected radiographically, for example, endodontically treated teeth that have been filled with post or silver points or conventionally filled root canal treatments that are short or inadequately condensed. If these teeth are symptomatic or if active infection is present, re-treatment is advisable.2
Surgical endodontic success rates have improved dramatically over the years with the development of newer retrofilling materials and the use of ultrasonic preparations. Previously cited success rates of 60% to 70% now have increased to more than 90% in many studies because of the routine use of ultrasonic retrograde preparation and the use of mineral trioxide aggregate as a filling material. This significant improvement makes apical surgery a much more predictable and valuable adjunct in the treatment of symptomatic teeth.3
This article describe a clinical case in which root canal retreatment was performed followed by root resection surgery with MTA as retrograde filling material.
CASE REPORT
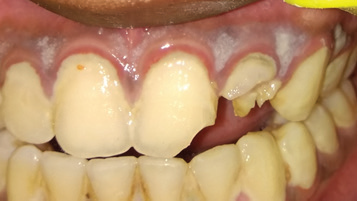
A 41 year old male patient reported to the Department of Conservative Dentistry and Endodontics with a chief complaint of pus discharge in the right anterior maxillary region since last 3 months. His second complaint was pain on touching and an intermittent swelling in the buccal aspect immediately above the gingival sulcus of right lateral incisor 12. He also complained of the discoloration of the lateral incisor of both the sides of the maxilla. He reported that 3 years back he had undergone the root canal treatment with fixed crown on the front two teeth. He also said an attempt to root canal retreatment was also performed in right upper central incisor 11 through crown 6 -months back. But no relief on swelling and pain was felt. Medical History: The patient is fit and well; the patient denied any major systemic disease. He had a history of tobacco chewing from past 10 years. The patient was amendable to local anesthesia and already has undergone prolonged dental procedures under local anesthesia. Radiographic examination revealed well defined radiolucency involving the coronally discolored maxillary right central incisor and lateral incisor. Teeth presented a negative response to pulp testing. The initial treatment plan proposed was orthograde retreatment. Need for surgical intervention for 12 and 21, if necessary, was explained to the patient and consent was obtained. After the removal of gutta-percha from the canals of 11,12,21,22 ,using K file (Mani, Japan) new working length was determined and thorough shaping and cleaning was performed . The teeth were then obturated using cold lateral condensation..Raising a Ochsenbein – Luebke (O-L) Flap, a periapical surgery was performed and periapical pathosis was enucleated Maxillary right central and lateral incisors were apically resected 3 mm from the apex and retrograde cavity was prepared using ultrasonic tip. MTA was placed as retrograde restorative material of 3 mm thickness. The placement of the retrograde filling material was confirmed using a radiograph and the sutures were placed. The patient was recalled after a week for suture removal.
The patient was kept under observation for the purpose of postoperative evaluation of healing of the periapical intervention in intervals of 1, 3, 6, 12, and 18 months.

Preoperative image with swelling I. R. T 11 and 12

Bleeding points marked

Flap raised

MTA Placement
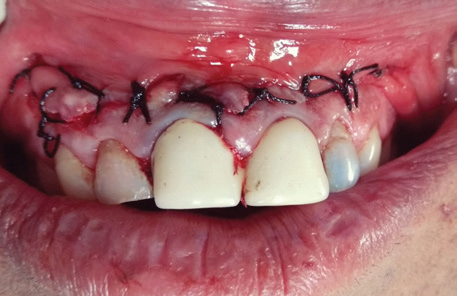
Suture Placed
RADIOGRAPHIC EVALUATION
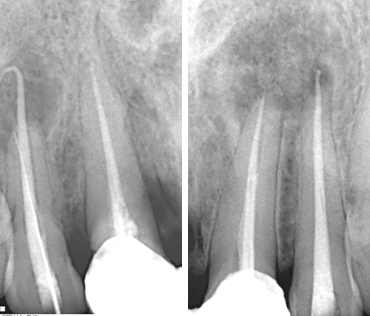
GP intentionally extruded in 12 and 22

After MTA Placement In 12
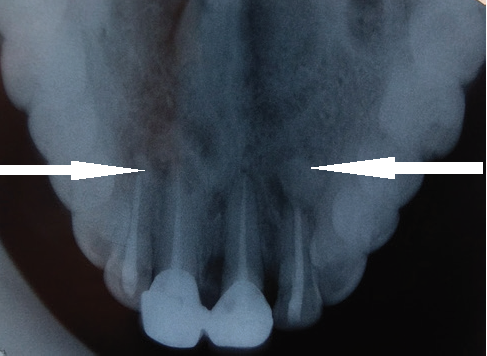
Follow up after 2 weeks
DISCUSSION
After the failure of the conventional root canal treatment (RCT), non-surgical retreatment is the preferred option in most cases. Several factors, such as a complex root canal system or previous procedural accidents, may impede the success of non-surgical retreatment.4 In this case, periradicular surgery and apicoectomy would be the treatment of choice to preserve the teeth. Hence,in the present caseroot end resection was performed and prepared, the root canal filling was placed within the created cavity to close the path of communication between infected root canal system and periradicular tissues. Using a root canal filling material with ideal properties has an immense effect on the treatment outcome of the surgery. An ideal material should be non-absorbable, non-corrosive, non-cytotoxic, not affected by moisture, dimensionally stable, biocompatible, antibacterial, radiopaque, cost-effective, easily manipulated, adhesive to dentinal walls, create a tight seal, and induce cementogenesis.4
Numerous materials have been recommended for root-end obturation, and many studies have attempted to identify an ideal material; however, an ideal material has not been found.5 The most commonly used materials are mineral trioxide aggregate (MTA) and IRM. Recent studies show that although IRM achieved the most favorable healing response, both radiographically and histologically, these results were not statistically different from MTA.6
The use of MTA as retrofilling material is justified because it has excellent physical properties is biocompatible with the periapical tissues and has the potential of conducting and inducing cementoblasts and osteoblasts, and the ability to release the main cationic components and trigger the surface of precipitates chemically and structurally similar to hydroxyapatite. The ability of MTA to induce the cellular response is due to the phase of calcium phosphate, which can cause a change in cell behavior, simulating the adhesion of osteoblasts to this material. In addition, the MTA is non mutagenic or non neurotoxic and produces no side effect on microcirculation.7,8
The initiation of surgery should be based purely on the selection of flap design, considering exposure of field, ease in surgery, assistance and finally good closure resulting in good healing and aesthetic scar. Many flaps have been introduced, but in gingival flaps, trapezoidal flap is favoured a lot due to its good visibility, easy stitching and handling. But since the introduction of this flap, the approximation of flap back in its original position, maintaining the interdental attachment and prevention of recession of gingiva after healing has not been accomplished. Now other flaps, like Semi lunar or Triangular flaps are considered as good as trapezoid. Since the introduction of the Ochsenbein – Luebke (O-L) Flap, oral surgeons tried this flap and found it better in many ways, such as ease in reflection of flap (as you have not to reflect the attached gingiva), no recession of gingiva and no fear of exposure of restorative margins,ease of stitching and good cosmetic results.9
In the present case it was justified Ochsenbein – Luebke (O-L) Flap have advantage over the Trapezoidal flap as it is easy to reflect, has good visibility, less bleeding duration and is easy to handle during surgery. Stitches are less time consuming, there is less tearing, better cosmetic result and no recession of gingiva.9,10
The drawbacks of MTA are related to difficulty in controlling the length of the filling, the chance of producing voids and the absence of solvent materialfor removal. Besides the presence of difficult handling, long setting time and high material cost. This was the limitation of this case report.
CONCLUSION
Apical surgery is now considered a predictable treatment option to save a tooth with apical pathology that cannot be managed by conventional, nonsurgical endodontics. Based on both the literature and the clinical case presented, it could be concluded that the use of MTA as a retrograde filling material in the endodontic surgery when well indicated and performed has a very favorable prognosis, which consequently eliminates the infection in the periapical area, allowing new bone formation.
REFERENCES
- Black CV. Amputation of the roots of teeth. In: Litch WF, editor. The American system of dentistry. Philadelphia: Lea Brothers; 1886. pp. 990-2.
- Samuel Paul Nesbo, Stephen J. Stefanac in Treatment Planning in Dentistry (Second Edition), 2007 .The Definitive Phase of Treatment.
- Shahme Ahmed Farook. Controversies In Office-Based Surgery. Maxillofacial Surgery (Third Edition)Volume 2, 2017, Pages 1447-1464.
- Asgary S, Ehsani S. Periradicular surgery of human permanent teeth with calcium-enriched mixture cement. Iran Endod J 2013;8:140-4. Pub Med PMC.
- Tawil PZ, Trope M, Curran AE, Caplan DJ, Kirakozova A, Duggan DJ, Teixeira FB. Periapical microsurgery: an in vivo evaluation of endodontic root-end filling materials. J Endod 2009; 35: 357-62. DOI Pub Med
- Lindeboom JA, Frenken JW, Kroon FH, van den Akker HP. A comparative prospective randomized clinical study of MTA and IRM as root-end filling materials in single-rooted teeth in endodontic surgery. Oral Surg Oral Med Oral Pathol Oral Radiol Endod 2005; 100:495-500. DOI Pub Med.
- Torabinajad Mineral Trioxide Aggregate: a comprehensive literature review - Part II: leakage and biocompatibility investigations. J Endod. 2010;36(2):190-202.
- Parirokh M, Torabinejad M. Mineral Trioxide Aggregate: a comprehensive literature review-Part III: clinical applications, drawbacks, and mechanism of action. J Endod. 2010;36(3):400-13.
- Gerstein H. Surgical Endodontics. In: Laskin DM. Oral and Maxillofacial Surgery, vol. 2, Indian edition, 1999 New Delhi C.V. Mosby Co., St. Louis Missouri USA, pp. 143-71.
- Kramper BJ, Kaminski EJ, Osetek EM, Heuer MA.A comparative study of the wound healing of three types of flap design used in periapical surgery. J Endodon 1984;10:17-25.
Disclaimer from Guident
The views and opinions expressed in articles published in Guident are solely those of the authors and do not necessarily reflect the views of the editors, the editorial board or the publisher, Ivory India. Guident does not endorse any product, technique or treatment described. Clinical content is intended for qualified dental and medical professionals and is not a substitute for individual clinical judgement. Guident, its editors and the publisher accept no liability for any consequence arising from the use of information published in the journal.
How to cite this article
Dr. Annil Dhingra, Dr. Shalini Sharma, Dr. Deepika Rawat. MTA - an Endodontic Boon in Healing of Periradicular Lesions. Guident. 2019 Jul;12(8). Available from: https://ivoryindia.in/articles/endodontics/mta-an-endodontic-boon-in-healing-of-periradicular-lesions.html