Surgical Management of Cystic Lesion
Department of Conservative Dentistry and Endodontics, Seema Dental College & Hospital, Rishikesh
Radicular cysts are the most common cystic lesions which affect the jaw. They are most common among all the jaw cysts and comprise about 52% to 68% of the entire cysts which affect the human jaw. They are generally symptomless and are diagnosed during routine radiologic investigations. The treatment of radicular cysts includes conventional nonsurgical root canal therapy when lesion is localized or surgical treatment like enucleation, marsupialization or decompression when lesion is large. This case report presents the successful surgical management of a large infected radicular cyst which was associated with maxillary central incisor and retained deciduous root.
CASE REPORT
A 25-year-old male patient reported to the Department of Conservative Dentistry, Seema Dental College and Hospital, Rishikesh, with chief complaint of swelling in palatal region of jaw, which had occurred 1 year back. Patient gave history of trauma in upper anterior teeth, which had occurred more than 5 years back.
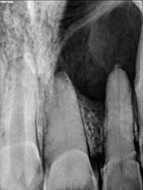
Intraoral clinical examination revealed a round to oval swelling which was located over labial mucosa of maxillary anterior region in association with 11, 21 and 22. Swelling was soft, localized, fluctuant, inflamed and nontender. A retained deciduous root as also seen associated with 21.
Treatment plan was formulated and after explaining it to the patient, his informed consent was taken. Root canal opening with 11, 21 and 22 was done under rubber dam application. Pus discharge was seen with 21 after access opening. After determination of working length and biomechanical preparation, calcium hydroxide intracanal medicament was used for one week. Then, in next appointment, obturation was completed.
Patient was prepared for surgery in next visit, which included surgical enucleation of cyst. After administration of local anaesthesia, incision was made in palatal region 15 to 25. A full thickness mucoperiosteal flap was reflected and a large bony defect with apex of 11, 21 and 22 was seen clinically along with retained deciduous root in relation with 21. Root was removed. Complete curettage, along with granulation tissue removal and enucleation of cystic lesion was done and it was sent for histopathological evaluation. Flap closure was done with 3-0 silk.
Post-operative instructions were given to the patient and patient was kept on antibiotics and analgesics. Currently, the patient is asymptomatic and he is under follow-up since 1 year. Follow-up radiograph showed appreciable healing.

Preoperative Image

Pre - Operative Radiograph

Working Length Determination

Master Cone

Obturation

Flap Reflection

Cystic Enucleation Was Done

Suture Placed

Post Operative Image
DISCUSSION
The term, cyst is derived from the Greek word Kystis, meaning, sac or bladder.1 Cyst is defined as a pathological cavity that is usually lined by epithelium and which has a centrifugal, expansive mode of growth.2
Radicular cysts are the most common cystic lesions which affect the jaw. They are most common of all the jaw cysts and comprise about 52% to 68% of all the cysts which affect the human jaw.3,4 They arise from epithelial remnants which are stimulated to proliferate, by an inflammatory process which originates from pulpal necrosis of a non-vital tooth. The natural history begins with a non-vital tooth which remains in situ, long enough to develop chronic periapical pathosis.5 They are most commonly found at the apices of the involved teeth. However, they may also be found on the lateral aspects of the roots in relation to lateral accessory root canals.6 They are symptomless and are diagnosed during routine radiologic investigations. The treatment for radicular cysts includes conventional nonsurgical root canal therapy when lesion is localized or surgical treatment like enucleation, marsupialization or decompression when lesion is large.7
Radicular cysts generally originate after trauma or dental caries. Dental caries cause inflammation of the pulp cavity, leading to pulp necrosis.8 The infection then spreads to the tooth apex of the root, causing periapical periodontitis, which leads to either an acute abscess or a chronic granuloma. Persistent chronic infection can lead to formation of a periapical cyst.9 In the current case, patient had given a history of trauma previously; it could be the probable aetiology.
Cortical expansion and root resorption of the affected tooth and displacement of the adjacent teeth are common features of radicular cysts.9 In the current case, there was cortical perforation and adjacent teeth in relation to the cyst were non-vital, which is not common. It has been stated that as the cyst enlarges, adjacent teeth can become non-vital.10
The use of root canal dressings between sessions in root canal treatment of teeth with chronic periapical lesions is important, for reducing bacteria which are unreachable by instruments or irrigation solutions, such as dentinal tubules and ramifications.11 Takahashi et al., after analyzing the pH and the concentration of calcium ions in the periapical area, concluded that at least 2 weeks were necessary for calcium hydroxide bactericidal activity.12 In the current case, calcium hydroxide intracanal medicament was used.
When the canal is wide and walls are parallel, the tapered shape of GP will not fit adequately. In such cases, it is necessary to roll three or more GP cones together on glass slab, in order to make a thick GP cone of even diameter.13 In the current case, tooth 21 presented with wide canals with open apex. It was successfully managed by roll cone technique obturation.
Due to the large size of the lesion, conservative surgical approach was planned. Conservative approach involves the removal of the infected tissues as compared to procedures like En bloc resection, which involves removal of the normal structure along with diseased tissue. The surgical approach to cystic lesions of the jaws is either marsupialization or enucleation. The treatment of choice is dependent on the size and localization of the lesion, the bone integrity of the cystic wall and its proximity to vital structures.14
Post-surgical period was uneventful. The histopathological features of the submitted lesion were consistent with the clinical diagnosis of infected radicular cyst. The cystic cavity was lined by nonkeratinized, stratified squamous epithelium with mixed inflammatory infiltration being present. Intracoronal bleaching, followed by composite restoration, was planned for
the patient. But patient was not interested in the restorative phase of the treatment due to economical reasons.
Healing of the periapical area has not yet been completed, due to large area of destruction. Currently, patient is asymptomatic and he has been kept under observation.
CONCLUSION
The current concept in management of periapical cysts is using nonsurgical means. However, depending on size and extent of lesion, surgical management might be necessary, for achieving success. Current case was managed successfully by performing endodontic therapy with thorough irrigation, cleaning and shaping and obturation of the canal space, followed by surgery.
REFERENCES
- PN Nair. New perspectives on radicular cysts:do they heal? Int Endod J. 1998;31:155–60.
- HF Sailer. Oral Surgery for the General Dentist. New York: Thieme; 1999. Pajarola GF.
- F Riachi, C Tabarani. Effective management of large radicular cysts using surgical enucleation vs. marsupialisation. IAJD. 2010;1:44–51.
- S Latoo, AA Shah, MS Jan, S Qadir, I Ahmed, AR Purra. Radicular cyst. J.K. Science. 2009;11:187–9.
- G Dimitroulis, J Curtin. Massive residual dental cyst: case report. Aust Dent J. 1998;43:234–7.
- PN Nair. Non-microbial etiology: periapical cysts sustain post-treatment apical Periodontitis. Endod Topics. 2003;6:96–113.
- RP Domingos, S Gonçalves Eduardo, S Neto Eduardo. Surgical approaches of extensive periapical cyst. Considerations about surgical technique. Salusvita Bauru. 2004;23:317–28.
- LM Lin, GT Huang, PA Rosenberg. Proliferation of epithelial cell rests, formation of apical cysts, and regression of apical cysts after periapical wound healing. J Endod. 2007;33:908–16.
- AL Weber, T Kaneda, SJ Scrivani, Jaw Aziz S. Head and neck imaging. 4th Edition. Mosby: St. Louis, MO; 2003. tumors and nontumorous lesions. In: Som PM, Curtin HD, eds; pp. 930–934.
- L Andersson, KE Kahnberg, MA Pogrel. Oral and Maxillofacial Surgery. Wiley: Blackwell; 2010.
- MR Leonardo, FF Silveira, LA Silva, M Tanomaru Filho, LS Utrilla. Calcium hydroxide root canal dressing histopathological evaluation of periapical repair at different time periods. Braz Dent J. 2002;13:17–22.
- Y Takahashi, T Yoshida, S Takashima. The regulation of intracellular calcium ion and pH in young and old fibroblast cells. J Gerontol. 1992;47:B65–70.
- Louis Grossman. Endodontic Practice. 11th Edition. Lea and Febiger Editor: Lea and Febiger Editor; 1988. p. 194. [Google Scholar]
- L Bodner. Cystic lesions of the jaws in children. Int J Pediatr Otorhinolaryngol. 2002;62:25–9.
- KT Koh. Mineral trioxide aggregate (MTA) as a root end filling material in apical surgery: a case report. Singapore Dent J. 2000;23:72–8.
- S Shahi. Comparison of the sealing ability of mineral trioxide aggregate and Portland cement used as root-end filling materials. J Oral Sci. 2011;53:517–22.
- I Islam, HK Chng, AU Yap. Comparison of the physical and mechanical properties of MTA and Portland cement. J Endod. 2006;32:193–7.
Disclaimer from Guident
The views and opinions expressed in articles published in Guident are solely those of the authors and do not necessarily reflect the views of the editors, the editorial board or the publisher, Ivory India. Guident does not endorse any product, technique or treatment described. Clinical content is intended for qualified dental and medical professionals and is not a substitute for individual clinical judgement. Guident, its editors and the publisher accept no liability for any consequence arising from the use of information published in the journal.
How to cite this article
Dr. Annil Dhingra, Dr. Shalini Sharma. Surgical Management of Cystic Lesion. Guident. 2019 Jun;12(7). Available from: https://ivoryindia.in/articles/endodontics/surgical-management-of-cystic-lesion.html