Growth Factors-Role in Periodontal Regeneration
Department of Periodontology, K.D. Dental College and Hospital, Mathura, Uttar Pradesh, India
ABSTRACT
A complex natural process is involved in regenerating periodontal structures lost during periodontal disease. The natural process includes relations between cells and growth factors. Growth factors are biologically active polypeptides affecting the proliferation, chemotaxis, and isolation of cells from epithelium, bone, and connective tissue. They express their action by binding to specific cell-face receptors present on target cells including osteoblasts, cementoblasts, and periodontal ligament fibroblasts. The use of growth factors has been considered an indispensable remedial modality to periodontal remedy because of their part in establishing and regenerating the periodontal tissues. The purpose of this composition is to review the literature concerning the natural conduct of colorful growth factors on periodontal cells involved in periodontal rejuvenescence.
Keywords: Growth factors, periodontal repair, periodontal regeneration, delivery systems, therapeutic application
INTRODUCTION
Periodontitis is the destruction of periodontal tissues, including cementum, bone, and periodontal ligament (PDL), and if left untreated ultimately tooth loss. Therapeutic modalities aim at barring the gingival inflammatory process and precluding the progression of the complaint along with re-establishing and regenerating the periodontal tissues. Studies targeted at understanding the disease at the cellular and molecular position as well as clinical examinations have redounded in bettered curatives for the arrest of disease progression also beyond the arrest of disease progression, substantial evidence exists indicating that regeneration of periodontal tissues is a feasible treatment for select situations. Periodontal regeneration is defined as the restoration of lost periodontium or supporting tissues and includes the formation of new alveolar bone, new cementum, and new periodontal ligament.1,3 Multitudinous growth factors have been linked and characterized.
Growth factor are the Proteins that may act locally or systemically to affect the growth and functions of cells in several ways. Growth factors are proteins that bind to specific receptors The overall scheme of how growth factors act depends on their mode of action. To elicit a natural effect, a growth factor must be synthesized by an forming cell, travel to its target receptor, interact with the target receptor or binding protein, and activate second messengers or terminal effectors. The biologic modifier is secreted from the first cell in a soluble manner and binds to receptors on the target cell to elicit its effects. Examples of this are the growth factors platelet-derived growth factor (PDGF) and transforming growth factor-ß (TGF- ß), which are produced by platelets and act on target cells similar as lymphocytes and osteoblasts. Autocrine factors are those that are synthesized by one cell, secreted in a soluble form outside the cell, then bind to surface receptors on the same cell to evoke an effect. Examples of autocrine factors are TGF-∞, which is produced and acts on epithelial cells, and the BMPs, which are produced and act on osteoblastic cells.2,4
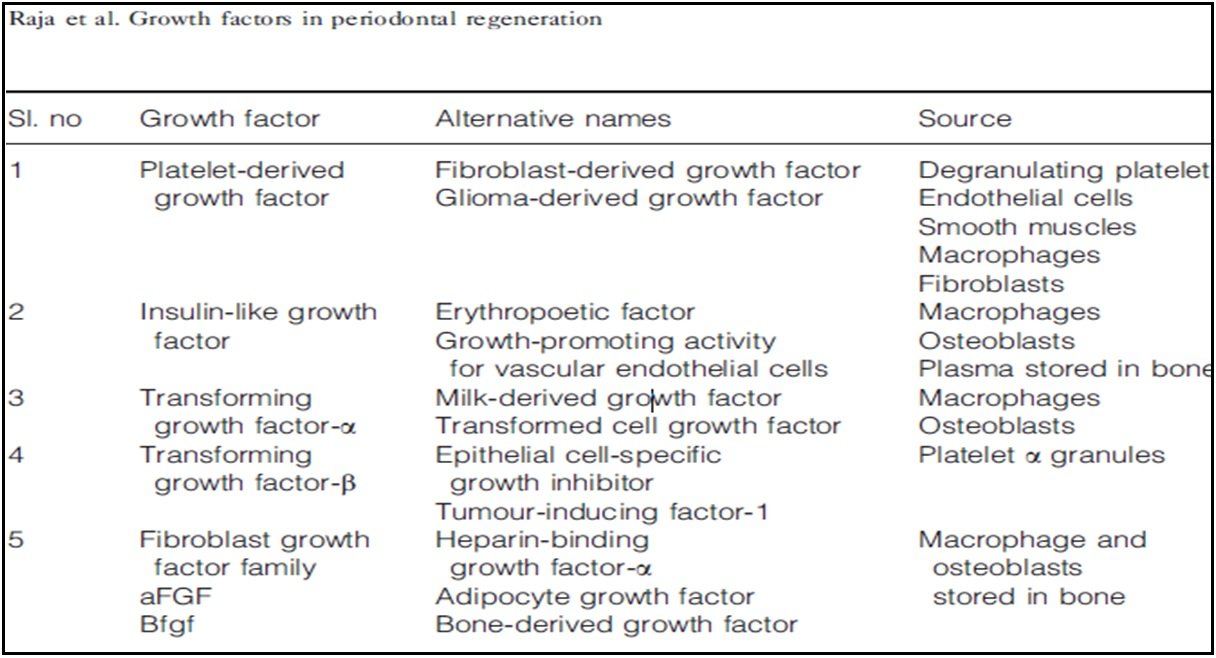
Table
The 1st growth factor was nerve growth factor identified by neurologist Rita Levi Montalcini in 1952. In 1962, Stanley Cohen, Professor in Biochemistry discovered the second growth factor – Epidermal Growth Factor (EGF).
PLATELET-DERIVED GROWTH FACTOR 8,9
The platelet-derived growth factor is a well-characterized protein. There are two different PDGF polypeptides that are 56 homologous and decoded by different genes. It has been set up to live in homo-dimer forms (PDGF- AA, PDGF- BB) as well as in heterodimer forms( PDGF- AB). It was discovered by Lynch and associates to promote the rejuvenescence of bone, cementum, and periodontal ligament in the late 1980s. There are two different PDGF receptors the PDGF- receptor ( binds PDGF- AA, PDGF- BB, and PDGF- AB) and the PDGF- ß receptor( binds PDGF- BB and PDGF- AB). The capacity of certain cells to respond to these PDGFs depends on the presence of these specific ∞ or ß receptors in the cells (Graves & Cochran, 1990). It has been demonstrated in rats that fibroblastic cells have both ∞ and ß types of PDGF receptors (Cho et al., 1994). PDGF has been insulated from a variety of cells and tissues, including monocytes and macrophages, fibroblasts, endothelial cells, and bone matrix. PDGF stimulates cells of mesenchymal origins, similar to fibroblasts, glia, smooth muscle, and bone cells. PDGF has been linked as a capability growth factor and acts synergistically with progression growth factors, similar to insulin growth factors. PDGF, still, also acts as a paracrine factor by stimulating certain cells to produce their own progression growth factors (Caffesse & Quinones, 1993).
IN VITRO STUDIES
Piche et al. (1989) demonstrated that PDGF stimulates the proliferation of cells from the periodontal ligament. The growth rate is dependent on the phenotype of the periodontal ligament cells; osteoblastic phenotypes gain more advance than fibroblastic phenotypes. Matsuda et al. (1992) reported also that PDGF has a mitogenic effect on periodontal ligament fibroblastic cells. These cells show a strong chemotactic response to PDGF. PDGF- AB stimulates collagen synthesis and PDGF- BB stimulates proliferation and chemotaxis. Park et al. (1995) used 6 beagle dogs to compare the result of guided tissue rejuvenescence around experimentally created vertical class III furcation defects with and without the use of PDGF- BB( result). The roots were demineralized with impregnated citric acid. Cho et al. (1995) introduced the" PDGF modulated guided tissue rejuvenescence remedy". This was an animal study of the beagle canine that repeated the same procedures as described in the study of Park et al.(1995). Lynch et al. treated 13 dogs with human recombinant PDGF- BB and insulin- suchlike growth factor ( IGF- I) in methylcellulose gel. At 5 weeks after surgery, the histologic analysis demonstrated a significant increase in new bone and cementum formation in the treated spots over that in control spots.10
INSULIN-LIKE GROWTH FACTORS 10,11
The insulin-like growth factors (IGF) are a family of single-chain serum proteins that partake 49 homologies in sequence with proinsulin. IGF- I and IGF- II are two polypeptides from this group that have been well described. They're synthesized by multiple tissues, including the liver, smooth muscle, and placenta, and are carried in tubes as a complex with specific binding proteins. These binding proteins may appreciatively or negatively affect the natural conditioning of IGF. IGF and their receptors can also be locally produced by osteoblasts. IGF has an analogous diapason of conditioning to those of insulin. IGF- I act as a progression factor. IGF has been shown to stimulate bone formation and to have an effect on periodontal ligament cells. It's believed that PDGF and IGF- I have a synergistic effect and that IGF- I alone don’t enhance bone formation. Clio et al. (1994) showed in conclusion that IGF- I have a mitogenic effect on PDL fibroblastic cells and is a potent chemoattractant for these fibroblasts.
In vitro studies by Hock et al. (1988) reported that IGF- I stimulate the formation of bone matrix in fetal rat calvariae in organ culture. They concluded that IGF- I stimulate bone formation by converting cellular proliferation and the secretion of extracellular matrix factors. Locally, IGF I and- II are produced by osteoblasts. Blom et al.(1992) demonstrated that IGF- I have a mitogenic effect on fibroblasts forming from connective tissues and cell lines and that IGF-I can stimulate the DNA synthesis of PDL fibroblasts, likely via binding to high-affinity cell surface receptors. In vivo studies, Lynch et al.(1989) studied the effect of the combination of PDGF and IGF- I in 3 beagle tykes and set up a horizontally naturally occurring bone loss in the dogs.
DanieloB. Palioto et al(2004) conducted a study to estimate the goods of EMD, IGF- I, and the combination of these two factors on the proliferation, adhesion, migration, and expression of type I collagen in PDL fibroblasts. The results showed that EMD, IGF- I, and a combination of both factors stimulated PDL fibroblast proliferation, whereas, these factors didn't affect adhesion, migration, and expression of type I collagen of these cells.12,13
TRANSFORMING GROWTH FACTOR 5,6
Transforming growth factor 3 is a member of a large family of biologically active protein hormones that are structurally related but differ markedly in their function. TGF-| 3 consists of 2 subunits held together by covalent bonds. Five different genes have been linked that render TGF- ß polypeptides. An inactive sphere of TGF- ß must be removed before TGF- ß is biologically active. It's activated by proteolysis and low pH. utmost of the cells express at least one of the TGF- ß genes. It's set up in high attention to platelets and in bone. TGF- ß appears to be a major controller of cell replication and isolation. It can stimulate or inhibit cell growth. It can modulate other growth factors similar as PDGF, EGF, and FGF. It inhibits epithelial cell proliferation and stimulates mesenchymal cells. It stimulates fibroblast chemotaxis and proliferation and induces extracellular matrix product. It has stimulatory and inhibitory goods on osteoblast proliferation. Matsuda etal.(1992) saw that TGF- ß induces inhibitory goods on mitogenic responses of the periodontal ligament cells. It reveals no chemotactic effect on these cells; still, TGF ß- stimulates the collagen synthesis. In vivo studies Selvig etal.( 1994) studied the goods of topical operation of a combination of IGF- II, ß- FGF and TGF- ß in a collagen sponger to treat experimentally created fenestration defects in 4 beagle dogs . At the control spots only collagen bloodsuckers as carriers were placed. Histometric analysis showed no differences in fibroblast and collagen viscosity between control and growth factor defects up to 14 days after surgery. Bone rejuvenescence was significantly lesser in control than in growth factor blights. This exemplifies how delicate it's to achieve a clinically effective combination of growth factors.
FIBROBLAST GROWTH FACTOR 13,14
There are 7 forms of fibroblast growth factors( FGF). Two are well described, one is introductory(b- FGF), the other acidic(a-FGF). The two fibroblast growth factors are products of different genes but are analogous in structure and function. These factors are potent mitogens and chemoattractive for endothelial cells and a variety of mesenchymal cells, including fibroblasts, osteoblasts, chondrocytes, smooth muscle cells and skeletal myoblasts. They're believed to act as capability growth factors and presumably need the synergistic action with progression growth factors to maximize DNA synthesis and growth( Caffesse & Quinones, 1993). These factors have important angiogenic effects in vivo(Thomas & Gimenez- Gallego, 1986). FGF binds tightly to heparan, a major element of the redundant ¬ cellular matrix. a-FGF and b- FGF are stored in the bone matrix( Hauschka etal., 1986) and may be important factors for the regulation of osteoblastic cells.In vitro studies Terranova etal. (1989) demonstrated that b- FGF stimulates mortal endothelial and periodontal ligament cell migration and proliferation, and that the combination with an attachment protein, fibronectin, further enhances periodontal ligament cell chemotaxis. They reported that b- FGF binds to native dentin and that this list is increased when the dentin is preconditioned with tetracycline HCI or citric acid( exposure of type I collagen). In vivo studies Eppley etal.(1991) examined the effects of autografts with or without| 3-FGF placed on irradiated bone resection sites in the mandible of animals. In the treated spots the mending and re-establishment of the mandible contour in half the creatures were observed, as well as a bone formation at the cortical perimeters adjacent to the growth factor recipient sites. . Nontreated spots resulted in sequestration, necrosis, and failure to heal. Shin- ki- Takayama et al( 2002) examined bFGF expression in gingival epithelium and the effect of bFGF on proliferative responses by gingival epithelial cells. They concluded that bFGF is anchored in the intercellular spaces of gingival epithelium via heparan sulfate and may regulate the growth and cytodifferentiation of GE cells via cell-type specific receptors.15,16,17
VASCULAR-ENDOTHELIAL GROWTH FACTOR (VEGF) 5,6
VEGF has been lately assayed from the GCF of a sampling of periodontal cases and healthy control subjects. Advanced situations of VEGF were set up in diseased spots than in healthy spots. In addition to its part in the regulation of angiogenesis, increases microvascular permeability. VEGF has also been lately suggested to play an important part in the regulation of bone remodeling by attracting endothelial cells and osteoclasts and by stimulating osteoblast isolation. Its possible role in periodontal disease progression was supported by a recent study reporting advanced VEGF attention in diseased gingiva adjacent to 4 – 6- mm pockets. Johnson RB et al 1999 suspected that VEGF may be an important factor in the progression of gingivitis to periodontitis through its part in promoting the expansion of the vascular network observed inflammation. Pelin Guneri et al( 2004) compared VEGF expression in healthy and periodontally diseased tissues with GCF of healthy and diabetic cases. Their study suggested that GCF VEGF values increased in periodontal spots of all test groups(DM).
EPIDERMAL GROWTH FACTOR 5,6
Epidermal growth factor( EGF) is a single-chain protein. The major sources of EGF are urine and salivary glands, although it also has been insulated from Brunner's glands and platelets as well as from cerebrospinal and amniotic fluids. EGF stimulates DNA synthesis and cell growth in a large variety of cells, including those of epithelial, endothelial, and mesodermal origin. still, EGF stimulates prostaglandin products and induces bone resorption in societies of neonatal mouse calvaria.
BONE MORPHOGENETIC PROTEINS 21,22,23
Bone morphogenetic proteins( BMPs) are osteoinductive factors that may have the eventuality to stimulate bone formation. Unlike the growth factors described over, the main action of BMPs is to stimulate undifferentiated pluripotential cells to separate into cartilage or bone-forming cells. In general, these factors don't stimulate the proliferation and migration of osteoblasts. It appears that there are at least 15 BMP- like molecules BMP- 1, BMP- 2, BMP- 3( osteogenin), BMP 4, etc. Another illustration is the osteoinductive protein(OP 1)( Lynch & Giannobile 1994). BMPs 2 to 7 are affiliated structural to TGF- ß, although the latter doesn't act like BMPs. Osteoinductive proteins were first insulated from a demineralized bone matrix. They can be produced by osteoblasts and stored in bone. Since both growth factors and BMPs are set up within the bone matrix, it is possible that demineralized freeze-dried bone contains small amounts of these proteins. The primary action of BMPs is to separate mesenchymal precursor cells into cartilage and bone-forming cells. BMP-2 induces the isolation of osteoblasts with the capacity to produce bone matrix proteins. BMP-3 ( osteogenin) induces cartilage formation preferentially to bone formation. BMPs 5, 6, and 7 compounds the capacity of BMP- 2 to form bone in vivo, although collectively they retain little bone-forming exertion. Because of this mode of action, rh BMP- 2 heals bony defects in a manner different from the other growth factors which have been used to increase bone mass. TGF- ß, IGF, and FGF all affect the formerly differentiated or committed bone-forming cells present in the bone, causing them to divide and/ or increase secretion of the extra ¬ cellular matrix molecules.
BMP IN PERIODONTAL REGENERATION 24
It may be reasonable to anticipate that BMPs also play a part in periodontal regeneration. Bowers et al.( 1991) set up that while osteogenin (BMP-3) augments new bone and cementum deposit around submerged teeth, it doesn't significantly enhance new bone or cementum formation around non-submerged teeth. nonetheless, Sigurdsson et al.(1995) studied the formation of bone and cementum rejuvenescence following periodontal reconstructive surgery using rh BMP-2 in six beagle dogs where they surgically created mandibular supra alveolar defects. During the mending period, the defects were submerged. At the test spots the rh BMP- 2 was applied with synthetic biodegradable particles and autologous blood. A possible explanation for the formation of new cementum after the operation of BMPs can be set up in Melcher's in vitro study( Melcher etal., 1987), in which cells insulated from bone were set up to synthesize cementum- suchlike and bone-like tissue in vitro.
DISCUSSION 18,19,20
Growth factors can be handed in large amounts using the recombinant ways. Further use of these factors in vivo studies is possible. There's a lot of hope that these growth factors can enhance periodontal rejuvenescence. still, healing of a periodontal lesion is a complex process. Variables similar as inflammation, smoking, systemic conditions and others can impact the effect of growth factors. Presumably, the growth factors need to be combined in a certain sequence for delivery and combinations of growth factors are demanded to give a synergistic effect. The attention used of the growth factor will be important, as will be the delivery system. therefore far, we can conclude from animal studies that the combined use of growth factors and the guided tissue regeneration gives good results and that PDGF and IGF are important growth factors for periodontal regeneration. Other future prospectives include:
- Using delivery systems: various agents used as sponges agents are Methylcellulose, Osseous grafts, Collagen gels, Collagen membranes and collagen- grounded sutures and hemostatic sponges or Synthetic polymer accoutrements . For partner. Using PGA materials to impregnate biologically active factors and control release of factors.
- Gene therapy: In this therapy the DNA of interest is generally driven via a protagonist from the viral vector, for illustration, to result in transcription of the gene of interest. frequently DNA is driven by a protagonist that's specific to the tissue of interest to insure expression in a designated area versus wide area.
- Cell based therapy: Cell based therapies are most generally associated with bone marrow transplantation strategies. The actual use of cell seeding in a periodontal operation has been limited to a pilot study using PDL fibroblasts in beagle dogs. Although favorable results were presented, including complete coverage of roots with cementoblasts, the study population was small, and extensive characterization would be necessary before this therapy could come to a clinical reality. There are two pathways for reestablishing periodontal regeneration. The first is the growth and migration of formerly differentiated cells into the wound site (alveolar bone cells and PDL cells), which can be determined by the use of growth factors. The alternate possible pathway is regeneration through the growth and differentiation of mesenchymal stem cells.
CONCLUSION
Regeneration of the periodontal tissues is a dynamic process involving cell-to-cell and cell–extracellular matrix relations. Growth factors elegantly coordinate together resulting in the healing of wounds and the regeneration of tissues. A combination of growth factors in an optimal concentration is best suited for periodontal regeneration. Several growth and isolation factors have shown to be implicit remedial agents although optimal dosage, release kinetics, and suitable delivery systems are still under exploration.
REFERENCES
- Lynch SE. The Role of Growth Factors in Periodontal Repair and Regeneration in ‘Periodontal Regeneration – Current Status and Directions’.Illinois, Quintessence, 1994.
- Graves DT, Cochran DL. Periodontal regeneration with polypeptide growth factors. Curr Opin Periodontol 1994; 2: 178–186.
- Stuart Jay Forum and Cynthia Gomez. Periodontal regeneration. Curr Opin Periodontol 1993; 1: 111–128.
- Howard T, Howell AA, Gianluca AA, Martuscelli AA, Richard J.Oringer polypeptide growth factors for periodontal regeneration.Curr Opin Periodontol 1996; 3: 149–156.
- Giannobile WV. The potential role of growth and differentiation factors in periodontal regeneration. J Periodontal 1996; 67: 545–553.
- Cochran DL, Wozney JM. 1999. Biological mediators for periodontal regeneration. Periodontol 2000 19:40–58.
- Raja et al. Growth factors in periodontal regeneration Int J Dent Hygiene 7, 2009; 82–89 87.
- Cho Moon OL, Wen-Langhin AA, Genco Robert J. Platelet derived growth factor – modulated guided tissue regenerative therapy.J Periodontol 1995; 66: 522–530.
- Cohen IK, Diegelmann RFLindblad WJ. Wound healing: biochemical and clinical aspects. Morgan & Jack Pledger, ‘‘Fibroblast proliferation’’pp. 63–74.
- Lynch SE, De Castilla GR, Williams RC et al. The effects of shortterm application of a combination of platelet-derived and insulin growth factors on periodontal wound healing. J Periodontol 1991; 62: 458–467.
- Rutherford RB, Niekrash CE, Kennedy JE, Charette MF. Plateletderived and insulin-like growth factors stimulate regeneration of periodontal attachment in monkeys. J Periodontal Res 1992; 27:285–290.
- Werner H, Katz J. The emerging role of insulin like growth factors in oral biology. J Dent Res 2004; 83: 832–836.
- Han X, Amar S. IGF-I signalling enhances cell survival in PDL fibroblasts vs gingival fibroblasts. J Dent Res 2003; 82: 454–459.
- Miki Y, Shimabukura Y, Kitamura M, Takayama S. The effect of application of bFGF on regeneration of the periodontal tissues.J Periodontal Res 1997; 32: 667–675.
- Takayama S, Murakami S, Shimabukuro Y, Kitamura M, Okada A.Periodontal regeneration by FGF-2 (bFGF) in primate models.J Dent Res 2001; 80: 2075–2079.
- Sato Y, Kikuchi M, Ohata N, Tamura M, Kuboki Y. Enhanced cementum formation in experimentally induced cementum defects of the root surface with the application of recombinant bFGF in collagen gel in vivo. J Periodontol 2004; 75: 243–248.
- Baird A, Ornitz DM. 2000. Fibroblast growth factors and their receptors. In: Canalis E, editor. Skeletal growth factors. Baltimore: Lippincott Williams and Wilkins. p 167–178.
- Bartold PM,McCulloch CA, Narayanan AS, Pitaru S. 2000. Tissue engineering: A new paradigm for periodontal regeneration based on molecular and cell biology. Periodontol 2000 24:253–269.
- X. E. Dereka et al. Role of growth factors on periodontal repair, December 2006; 24(4): 260–267
- Smith et al. Research on growth factors in periodontology; Periodontology 2000, Vol. 67, 2015, 234–250.
- Ripamonti U, Renton L. Bone morphogenetic proteins and the induction of periodontal tissue regeneration. Periodontol2000 2006;41:73-87.
- Ripamonti U, Duneus N. Tissue Morphogenesis and Regeneration by Bone Morphogenetic Proteins. Plastic and Reconstruct Surg 1998;101:227-339.
- Hollinger JO, Buck DC, Bruder SP. Biology of bone healing: Its impact on clinical therapy. Lynch 30-40.
- Wozney AM. The potential role of bone morphogenetic proteins in periodontal reconstruction. J Periodontol 1995:66:506-510.
Disclaimer from Guident
The views and opinions expressed in articles published in Guident are solely those of the authors and do not necessarily reflect the views of the editors, the editorial board or the publisher, Ivory India. Guident does not endorse any product, technique or treatment described. Clinical content is intended for qualified dental and medical professionals and is not a substitute for individual clinical judgement. Guident, its editors and the publisher accept no liability for any consequence arising from the use of information published in the journal.
How to cite this article
Dr. Ankita Garg, Dr. Shailendra S. Chauhan, Dr. Satendra Sharma. Growth Factors-Role in Periodontal Regeneration. Guident. 2023 Feb;16(3). Available from: https://ivoryindia.in/articles/periodontics/growth-factors-role-in-periodontal-regeneration.html